

This is Part 2 of a four-part series on the Stanford Consumer Health Conference. Part 2 goes deeper into the panels, the quotes, and the open questions that surfaced on the day. Read Part 1 (the origin story) here.

The conference was built around a single question: what does the next decade of consumer-empowered care look like? Over eight hours of panels, keynotes, and hallway conversations, a more specific version of that question kept surfacing: the innovation, investment, and awareness are increasingly there — so what’s actually still missing?
A second question came up for me, and I shared it in my keynote: what needs to be true to close the gap and cross the chasm so that all this investment in consumer-empowered care moves the needle on population-wide, systemic health issues?
What follows is my attempt to capture the most substantive ideas from the day, organized by themes that cut across sessions rather than panel by panel. I’ve included direct quotes from speakers and attendees where I can, and I’ve tried to be honest about where I think the industry is strong, where it’s still falling short, and what questions remain open.
The shift is real — and it’s structural, not just rhetorical
Dr. Daniel Kraft opened the day with a keynote on Medicine 3.0 that set the tone: digital twins, advanced wearables, AI diagnostics, virtual and augmented reality, gene editing. The vision was expansive — and intentionally so. His energy was infectious, and more than one attendee told me afterward that it “set the tone for the rest of the day with a lot of curiosity and engagement.”
The macro thesis he laid out was echoed in nearly every session that followed: healthcare is moving from episodic, hospital-centered treatment to continuous, consumer-controlled, data-driven prevention. As one attendee summarized it: “reactive to preventive, episodic to continuous, institutional to consumer-controlled, analog to data-driven.”
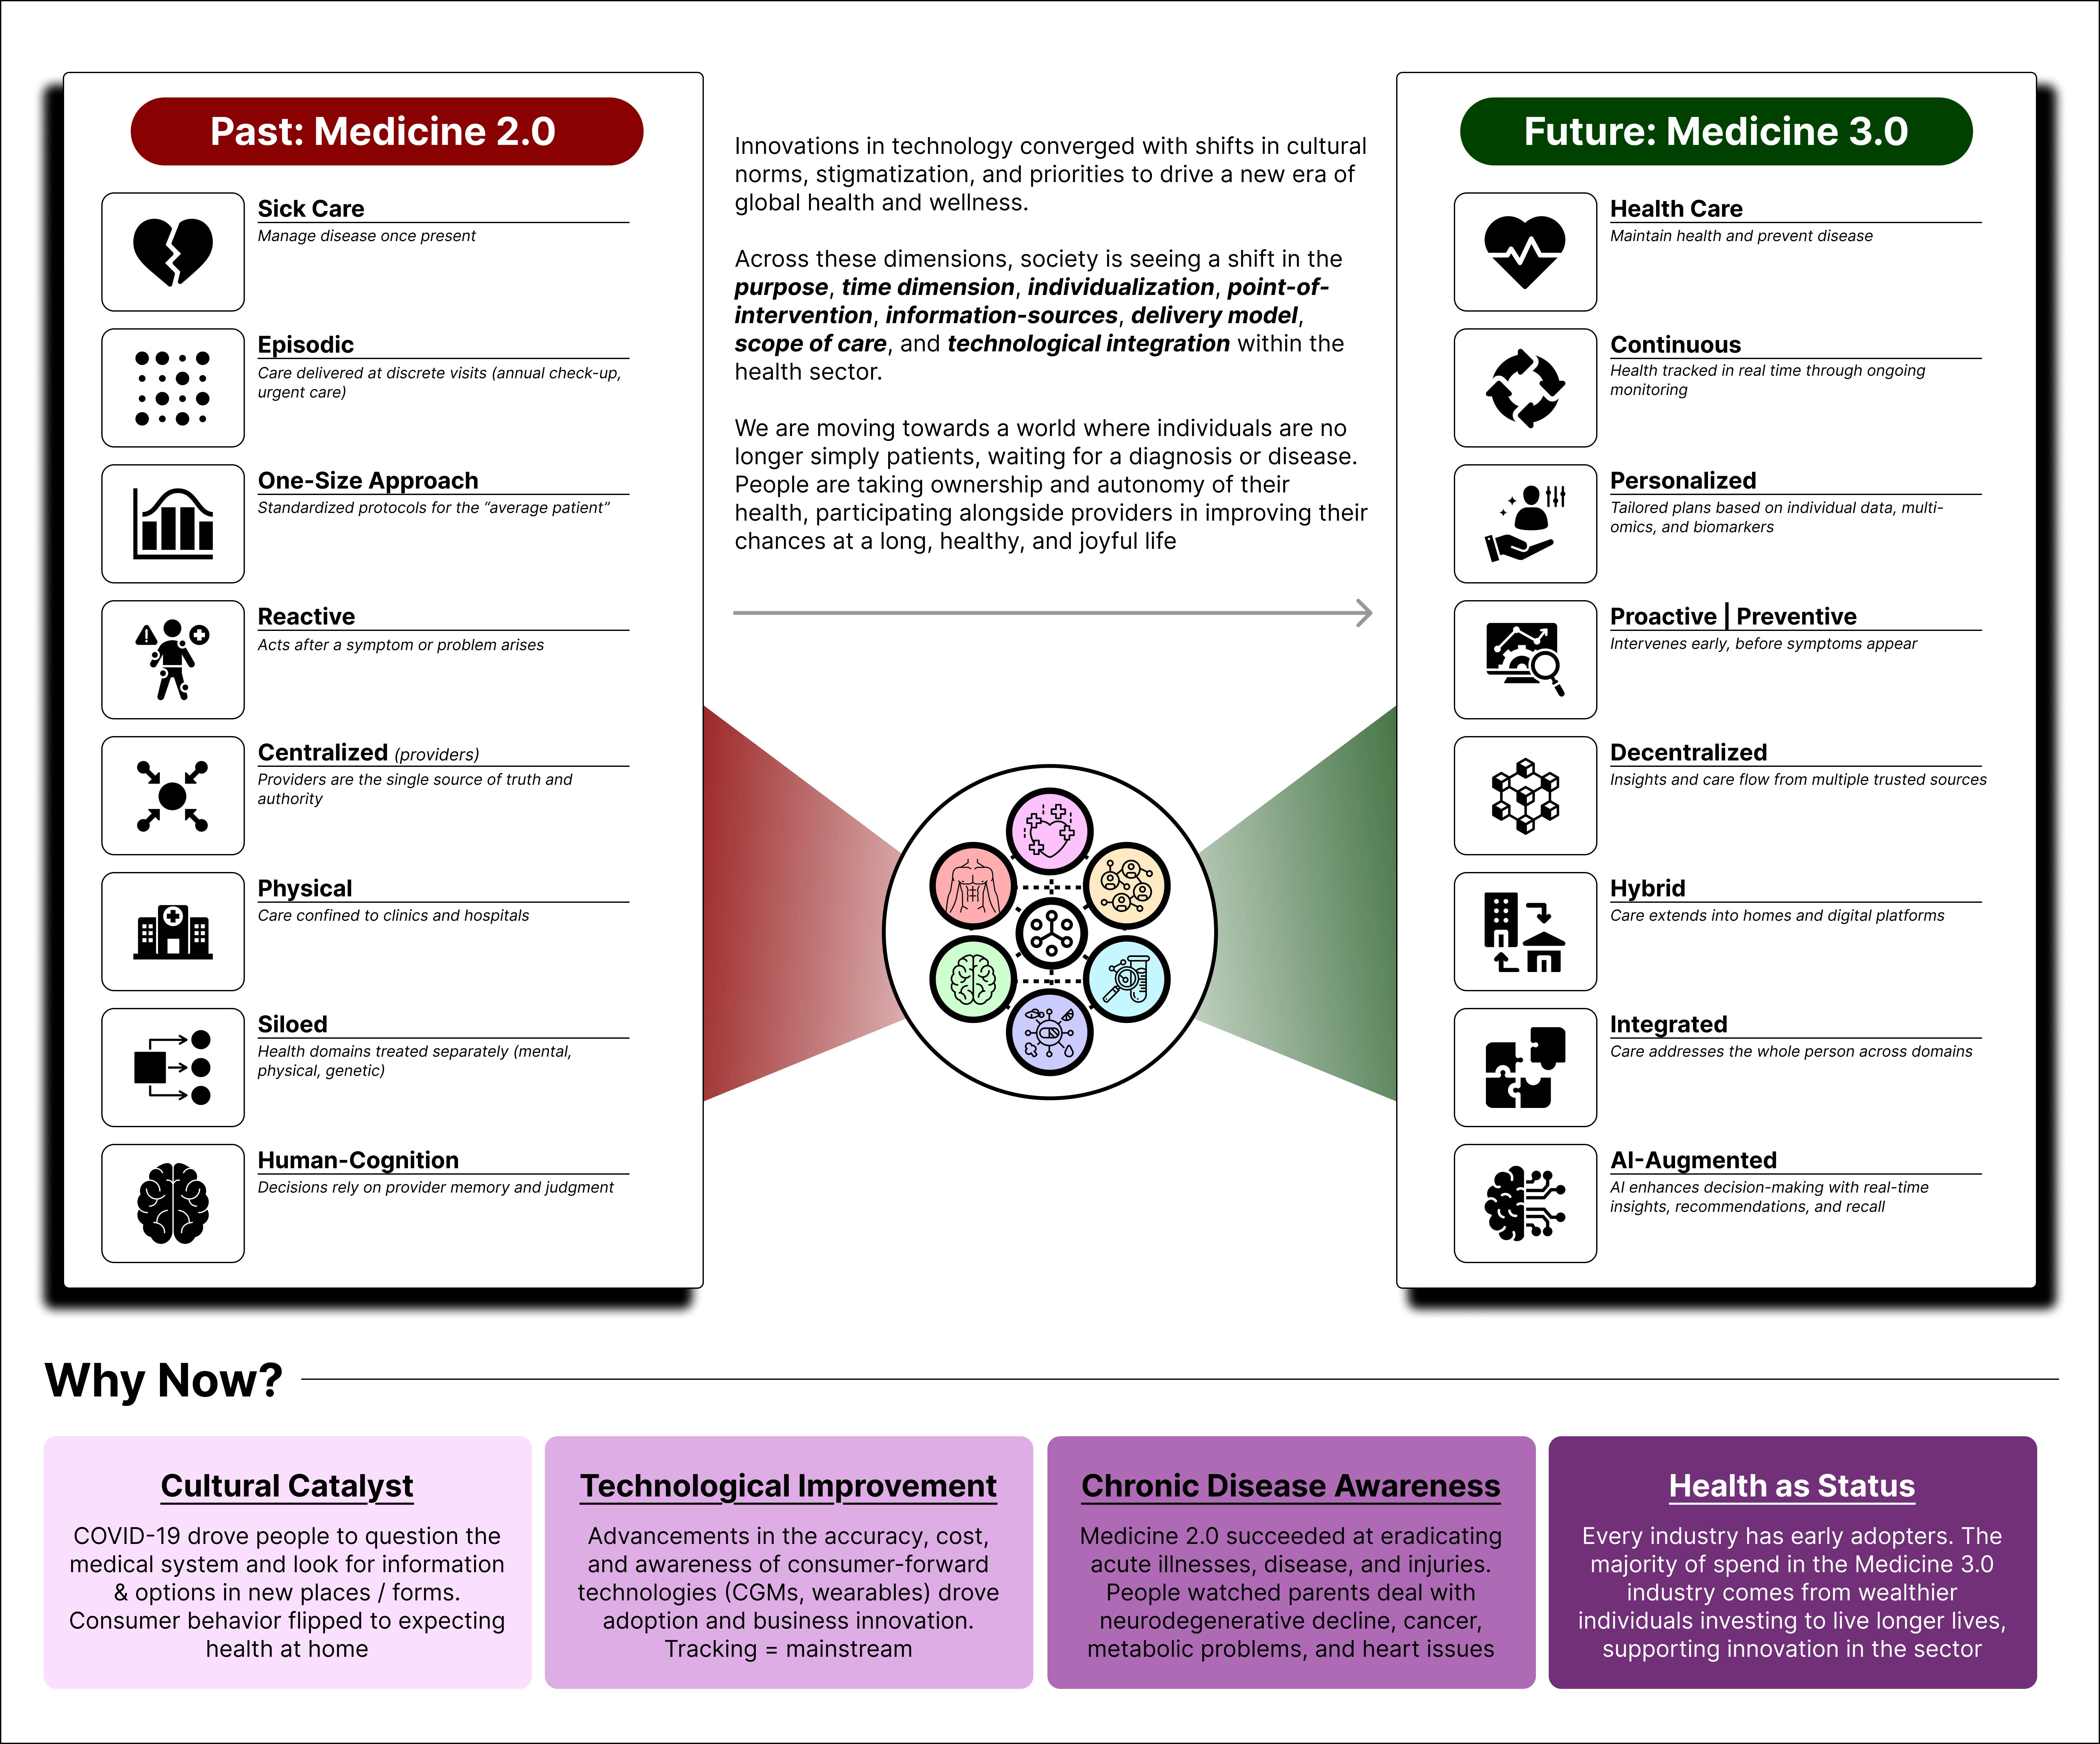
But the more interesting conversation was about what sits between that vision and reality. As a panelist quoted during the day: “97% of the $5.3T U.S. healthcare spend goes toward chasing disease, and only 3% goes to prevention.” We have built an almost perfectly reactive system. Rebuilding it will require more than good technology. It will require proving the economics, changing behavior at scale, and navigating regulatory frameworks that were not designed for this moment.
Several speakers noted that many consumer health companies don’t fit neatly into a single regulatory category — not purely a medical device, not purely a wellness tool, not a traditional provider. Thoughtfully navigating that gray zone is critical to durability.
Trust as strategy, not sentiment
If I had to name one word that defined the day, it would be trust. Not as a branding exercise — as an operational strategy.
Dr. Ricky Bloomfield, CMO of Oura, was direct: “Behavior change is real. The information equips you to make a choice. We don’t want you to be in a clinic; we want you to be at home enjoying your lives.” But he paired that with a harder point: if consumer health platforms want to be taken seriously, they must measure clinical outcomes and healthcare cost reduction — not just engagement metrics. Bridging credibility with clinicians is essential if consumer-generated data is to inform care.
Christopher Gardner, Stanford professor of medicine, framed it most starkly: “The tech is ahead of the science, and the science is trying to catch up. If we don’t have the science to back up the products, they will never be complete, and people will be distrustful.”
The longevity panel made this tangible. Chris Mirabile, CEO of NOVOS, shared research showing that combining certain longevity supplements often produces negative interactions: “What’s the point of taking a longevity supplement if you’re wasting time? That’s the antithesis of longevity.” One of the soundbites I took away was: “Sometimes, 1+1 = 0.” NAD, trending supplement protocols, and heavily marketed biohacking products are running ahead of peer-reviewed validation. That gap is a real risk. Consumer trust, once broken, is hard to rebuild.
The companies that are investing in science now — Oura, WHOOP, Noom, Eight Sleep, January AI — are building a moat that marketing cannot replicate. Geoff Cook shared that Noom will invest $10 million in research in 2026 alone. “Clinical-grade evidence is becoming table stakes. Science is a moat.”
An open question I keep returning to: what is the actual difference between science/medicine and wellness? Where are the barriers between the two? How will these industries work together? And how do we keep moving toward the truth? In an era of AI, misinformation, and distrust, how do we properly inform individuals about the best ways to manage their long-term, proactive health?
Data is abundant. Meaning is scarce. The “Health OS” is coming — slowly.
“Data is the marketing for medicine,” said Geoff Cook. With more than 50% of Americans now using wearables and at-home diagnostics surging, data alone is no longer the differentiator. “Data is everywhere, but meaning is missing. It is becoming abundantly clear that the winners in this industry are those who either integrate seamlessly into customers’ existing lives or find a way to change consumer behavior with generated data.
Alex Vannoni from WHOOP described what translation looks like in practice: trust means seeing results and outcomes, which leads to sustained engagement. Creating those “magical moments” through high-fidelity health data and relevant insights builds confidence. A clear example of this is customers’ relationship with alcohol, Whoop/Oura, and sleep. The feedback loop of having a drink and seeing sleep score plummet is immediately apparent. Consumer health products can be a “check engine light” for health — alerts that draw attention but stay invisible otherwise.
Matteo Franceschetti of Eight Sleep painted the near-future: users don’t want to learn multiple apps. People want to understand what matters to them, which means creating more data that their personal health agent can rely on. His vision of a home-based health agent that doesn’t just monitor but acts on your behalf was one of the most discussed ideas of the day. As one attendee wrote: “I thought the idea of personalized consumer dashboards built with custom AI agents that bring together data from a variety of different data sources was super interesting.”
Ricky Bloomfield described how Oura is approaching this from an open infrastructure perspective: the personal health OS will be truly personal, built by members who are already creating their own experiences via the API. The discussion around a personal Health OS is not new, with countless startups racing to be your one-stop shop for all your health information and guidance.
But the investor panel applied healthy skepticism. Holly Maloney, Alison Ryu, Julie Yoo, and Kurt Seidensticker reinforced that blending data across wearables, sleep devices, CGMs, EHRs, and nutrition logs is far more complex than marketing suggests. Fragmentation is not disappearing. The opportunity may not be the aggregator, but the infrastructure layer that makes aggregation usable.
Alison Ryu framed the AI opportunity with precision: “The real AI opportunity isn’t the AI doctor. It’s the orchestration layer — AI that knows your context, maintains continuity, and routes you to the right intervention at the right moment, bringing a high-quality human into the loop when the stakes demand it.” She added, “I don’t think one super app wins. I’m more bullish on condition-anchored platforms that earn deep trust in a high-acuity domain first, then expand from a position of demonstrated clinical credibility.”
Holly Maloney added that fragmentation isn’t a problem to be solved — it’s infrastructure to be built.
GLP-1s: a window, not a solution
Geoff Cook’s framing of GLP-1s was one of the most-discussed ideas of the entire conference. “People are using GLP-1s as a window for change.”
The data behind it: 11 out of 12 people separate from GLP-1 medications by year 3. Without lifestyle change, the weight comes back. GLP-1s can never be the whole solution. But for Noom, GLP-1 therapy is a catalyst — temporarily altering appetite and food noise, opening a window to build durable skills and routines. A full third of people signing up for Noom plans were previously on a GLP-1. People want whole-person health. They want to combine habit science with change catalysts to make lasting change feel easier.
Geoff’s deeper point was that what actually drives lasting change is mastery experiences. GLP-1s boost perceived control, self-efficacy, and ability. What else does that? Shifts in routines, self-efficacy, and ultimately identity — changes that can survive medication discontinuation. People want lasting change, not just a prescription.
Cheryl Hoy captured it well in her recap: “Medication can accelerate progress, but lasting health still requires lifestyle change. There is no such thing as a ‘free lunch,’ even if you don’t eat any.”
The strongest interventions meet people in moments of transition — perimenopause, postpartum, metabolic inflection points, injury or diagnosis, major life stressors. Start with high motivation and true personalization, then design for sustainable habits. Evidence builds trust. Trust drives integration across providers, payers, and employers. Integration enables sustainability.
Community as a health intervention
Perhaps no theme surprised me more than the role of community. In a conference heavy on data, AI, and clinical infrastructure, the most emotionally resonant sessions were about belonging.
Dr. Jonathan Leary, CEO of Remedy Place, described the paradox: “The healthier I got my patients, the more isolating their lifestyle became. That’s where the birth of social self-care was.” Health can feel like a sacrifice for our social life, which is exactly why Remedy Place was built: to create social connections over shared experiences of doing things that are good for your body.
Bryan Myers reflected on the power of pushing your body to its limits and how that builds deep bonds with others — the importance of shared discomfort. Douglas Gremmen shared how HYROX creates an environment that feels personal even as it grows globally — building intimacy at scale as a growth tactic. Leaders from HYROX, [solidcore], Eudemonia, and Remedy Place agreed: the future of fitness and wellness broadly is social, communal, and built around belonging.
This wasn’t soft science. Multiple attendees flagged community as the thing that drives retention more than any product feature. The companies that have made healthy behavior a social behavior are the ones people don’t leave. Plus, what is the point of getting healthier if not to enjoy life with others?
The investor lens: LTV, not just growth
The investor panel with Julie Yoo (a16z), Holly Maloney (General Catalyst), Alison Ryu (Able Partners), and Kurt Seidensticker (Starshot Ventures) was one of the highest-rated sessions of the day.
Alison Ryu’s framework was specific: “DTC first is a viable strategy with the right unit economics. Stay there longer than you think you need to. Enterprise can be a graveyard: long sales cycles, pilots that never convert, roadmaps distorted toward the buyer rather than the user. Founders who enter an employer or payer conversation with 50K paying subscribers and two years of retention data are in a fundamentally different position than those who arrive with a deck and a pilot offer.”
On retention: “The best consumer health companies are sticky because leaving costs the user something real: a result they’ve achieved, an insight they rely on, a relationship they value, or an identity they’ve built.” Treat your early members like VIPs — they are your best source of product feedback and organic word-of-mouth. Find the 1000 people that absolutely LOVE your product.
On the economics of prevention: “The ROI case for prevention is finally real, and AI is what changed it. For the first time, you can build a counterfactual at the individual level and put a dollar value on it. Together with longitudinal behavioral data, they unlock a genuine economic case for prevention that a self-insured employer or payer will actually act on.”
Warren Shaeffer called it the “Tesla Roadster” phase of consumer health: the tech is powerful and exciting, but broad access isn’t here yet. Costs will come down. And as Julie Yoo pointed out, consumer health itself was considered a niche or “non-serious” category not long ago. Today, some of the most durable, venture-scale companies are being built precisely in areas that were once taboo — gut health, hormones, sleep optimization.
AI and mental health: urgency meets evidence
Headspace Chief Product Officer Fay Kallel articulated the tension the entire industry is navigating: “People have already turned to these technologies for mental health support. It’s not responsible for us to wait until we have fully built evidence systems — we need to provide support now, with rigorous guardrails in place.”
This was one of the more nuanced panels of the day. The mental health space is moving fast, with AI-powered tools reaching people who might never see a therapist. But the evidence base is still being built, and the stakes of getting it wrong are high. The consensus was not that we should slow down — it was that speed and rigor need to coexist.
Open questions
Not all questions were answered during the conference. A few critical questions still loom large in my mind, and hopefully are being discussed at a deeper level as a result of this event. Those include:
Business Implications
What are the actual sustainable business strategies? How are these companies driving true behavior change, retention, and user engagement?
Is the only way to exist in ten years through integration with the existing healthcare infrastructure, where insurance or the government pays for the technology or service (e.g., Oura, WHOOP)?
Driving true systemic and population impact
My keynote question still rings top of mind, and is something I want to carry into all my research and conversations going forward: how do we actually make an impact? How do we serve the people who actually need these technologies, services, and tools, but who can’t afford them?
What do companies need from scientists, regulators, and policymakers to reset the system?
Delineating wellness vs. medicine
What is the actual difference between science/medicine and wellness? Where are the barriers, how will the industries work together, and how will we keep moving toward truth?
What is the right way of empowering consumers with information and tools? In an era of AI, misinformation, disinformation, and distrust, how can we properly inform individuals about the best ways to manage their long-term, proactive, holistic health?
These questions weren’t answered during the conference. But the fact that they were raised — by founders and investors, not just academics — felt significant. The industry knows these gaps exist. Whether they close will define whether consumer health becomes a movement or stays a market segment.
Next week: Part 3 — The Playbook. A step-by-step guide to building a conference from zero.
Interested in attending or getting involved in next year’s conference? Sign up here: https://forms.gle/tBqzqdGgdrW9qEtj9
interesting that you’re saying science is a moat. i’ve always wondered how i will eventually fund research for deep cellular cleansing + detoxification and the fundamental truth that toxicity is a root cause of many common health symptoms and chronic diseases. it’s hard to push that narrative forward without “being backed by science”, it the problem is that it takes decades for the science to catch up.